

Efficacy data of ICLUSIG (ponatinib) in newly diagnosed Ph+ ALL
PhALLCON TRIAL DATA
Study design: PhALLCON was the first head-to-head phase 3 clinical trial vs another TKI in adults with newly diagnosed Ph+ ALL1,2
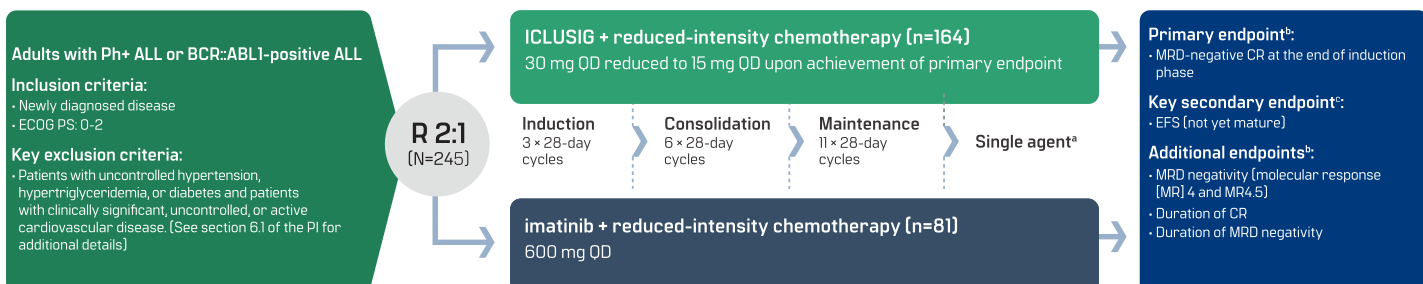
Only patients who achieved the primary endpoint of MRD-negative CR or CRi at the end of induction could continue study treatment at the investigator’s discretion1
- Single-agent therapy after chemotherapy for newly diagnosed Ph+ ALL is not an approved regimen1
*Following combination therapy, patients continued to receive ICLUSIG or imatinib as single-agent therapy until relapse from CR, progressive disease (PD), hematopoietic stem cell transplantation (HSCT), start of alternative therapy, or unacceptable toxicity.1
†MRD negativity was defined as ≤0.01% BCR::ABL1/ABL1 or undetectable BCR::ABL1 transcripts in cDNA with ≥10,000 ABL1 transcripts. BCR::ABL1/ABL1 levels were reported as an absolute (raw) ratio for the p190 variant test and on the International Scale (BCR::ABL1IS) for the p210 variant test. Patients were considered to achieve CR if they maintained/had no circulating blasts and <5% blasts and normal maturation of all cellular components in the bone marrow, no extramedullary disease (ie, central nervous system involvement, lymphadenopathy, splenomegaly, skin/gum infiltration, testicular mass), and ANC ≥1000/mcL, and platelets ≥100,000/mcL for at least 4 weeks. Patients who met both criteria were considered to have achieved MRD-negative CR.1
‡EFS defined as dates of randomization until death due to any cause, failure to achieve CR by the end of induction, or relapse from CR.3
ALL=acute lymphoblastic leukemia; ANC=absolute neutrophil count; cDNA=complementary DNS; CNS=central nervous system; CR=complete remission/response; CRi=incomplete hematologic response; ECOG PS=Eastern Cooperative Oncology Group performance status; EFS=event-free survival; MRD=minimum residual disease; Ph+ ALL=Philadelphia chromosome-positive acute lymphoblastic leukemia; PI=prescribing information; PO=per os; OD=once daily; SCT=stem cell transplantation; TKI=tyrosine kinase inhibitor.
Reduced-intensity chemotherapy regimens
Reduced-intensity chemotherapy regimens
- Induction (3 x 28-day cycles)1
- Vincristine 1.4 mg/m2 (capped at 2 mg) intravenously (IV): Days 1, 14
- Dexamethasone 40 mg (<60 years), 20 mg (≥60 years) orally (PO): Days 1-4, 11-14
- Consolidation (6 x 28-day cycles)1
- Methotrexate 1000 mg/m2 (<60 years), 250 mg/m2 (≥60 years) IV: Day 1 on Cycles 4, 6, 8
- Cytarabine* 1000 mg/m2 (<60 years), 250 mg/m2 (≥60 years) IV: Days 1, 3, 5 on Cycles 5, 7, 9
- Maintenance (11 x 28-day cycles)1
- Vincristine 1.4 mg/m2 (capped at 2 mg/m2) IV: Day 1 of each cycle
- Prednisone 200 mg PO (<60 years), 100 mg PO (≥60 to 69 years), 50 mg PO (≥70 years) on Days 1 to 5
CNS prophylaxis was administered on Day 1 and Day 14 of the 3 induction phase cycles and the first 3 consolidation phase cycles (total: 6 cycles, 12 intrathecal injections) and comprised a triple intrathecal injection of methotrexate, cytarabine, and corticosteroids. If patients moved to the maintenance phase directly from induction or before completing consolidation, they were still required to receive the complete course.2
*Every 12 hours.
ICLUSIG: For the range of appropriate patients you see in your practice1
Baseline patient and disease characteristics were well balanced across arms1,2
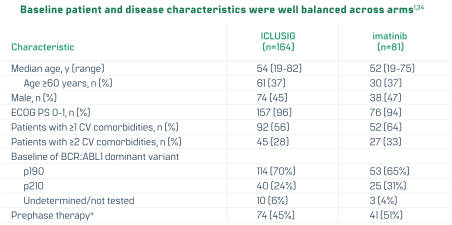

aPer protocol, patients were allowed to receive one cycle of optional prephase therapy excluding TKI prior to randomization.1
CV=cardiovascular; ECOG PS=Eastern Cooperative Oncology Group performance status; Ph+ ALL=Philadelphia chromosome-positive acute lymphoblastic leukemia; TKI=tyrosine kinase inhibitor
Significantly superior rate of MRD-negative CR with ICLUSIG vs imatinib at the end of induction (primary endpoint)1
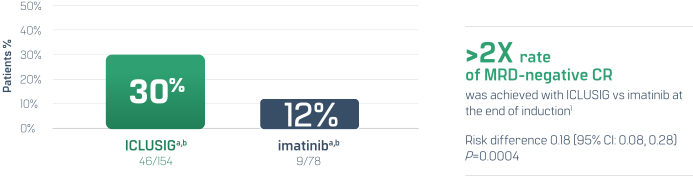
- MRD-negative CR is defined as ≤0.01% BCR::ABL1/ABL1 or undetectable BCR::ABL1 transcripts in cDNA with ≥10,000 ABL1 transcripts, and meeting criteria for CR.*
bTreatments were used in combinations with chemotherapy.1
*BCR::ABL1/ABL1 levels were reported as an absolute (raw) ratio for the p190 variant test and on the International Scale (BCR::ABL1IS) for the p210 variant test. Patients were considered to achieve CR if they maintained/had no circulating blasts and <5% blasts and normal maturation of all cellular components in the bone marrow, no extramedullary disease, ANC ≥1000/mcL, and platelets ≥100,000/mcL for at least 4 weeks. Patients who met both criteria were considered to have achieved MRD-negative CR.2
ANC=absolute neutrophil count; cDNA=complementary DNA; CI=confident interval; CR=complete remission/response; EFS=event-free survival; MRD=minimal residual disease.
ICLUSIG delivered a higher rate of MRD negativity* vs imatinib at the end of induction (additional endpoint)2
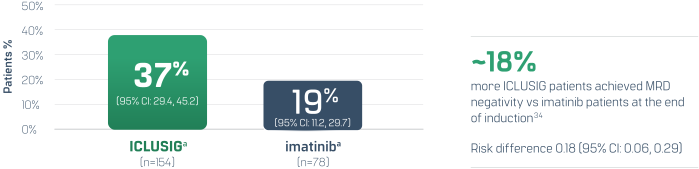
- Limitations: PhALLCON was designed to show a statistically significant difference between arms for MRD-negative CR;* the trial was not designed to show a statistically significant difference between arms for MRD-negativity alone1,2
†Treatments were used in combination with chemotherapy.1
CI=confidence interval; CR=complete remission/response; MR=molecular response; MRD=minimal residual disease.
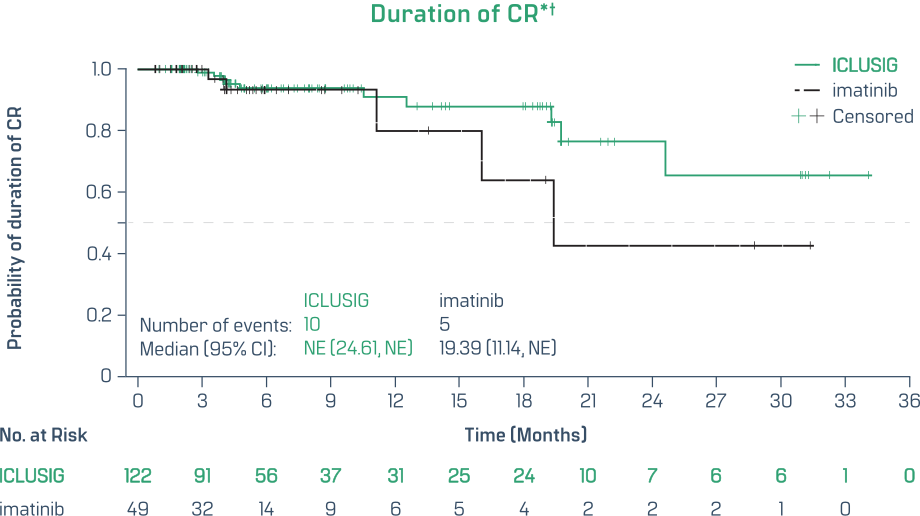
ICLUSIG extended the duration of complete remission vs imatinib2 (additional endpoint)
- Study features3,4
- The median duration of follow-up was 20.4 months (95% CI: 18.4, 23.9) with ICLUSIG and 18.1 months (95% CI: 13.9, 24.3) with imatinib
- Relapse from CR: 8.2% (n=10) of ICLUSIG patients vs 10.2% (n=5) of imatinib patients at the time of data cutoff (August 12, 2022)
- Limitations: PhALLCON was designed to show a statistically significant difference between arms for MRD-negative CR;‡ the trial was not designed to show a statistically significant difference between arms for duration of CR
†Complete remission is also known as complete response.
‡MRD negativity was defined as ≤0.01% BCR:ABL1/ABL1 or undetectable BCR::ABL1 transcripts in cDNA with ≥10,000 ABL1 transcripts BCR::ABL1/ABL1 levels were reported as an absolute (raw) ratio for the p190 variant test and on the International Scale (BCR::ABL1IS) for the p210 variant test.
ALL=acute lymphoblastic leukemia; CI=confidence interval; CR=complete remission/response; MRD=minimal residual disease; NE=not evaluable
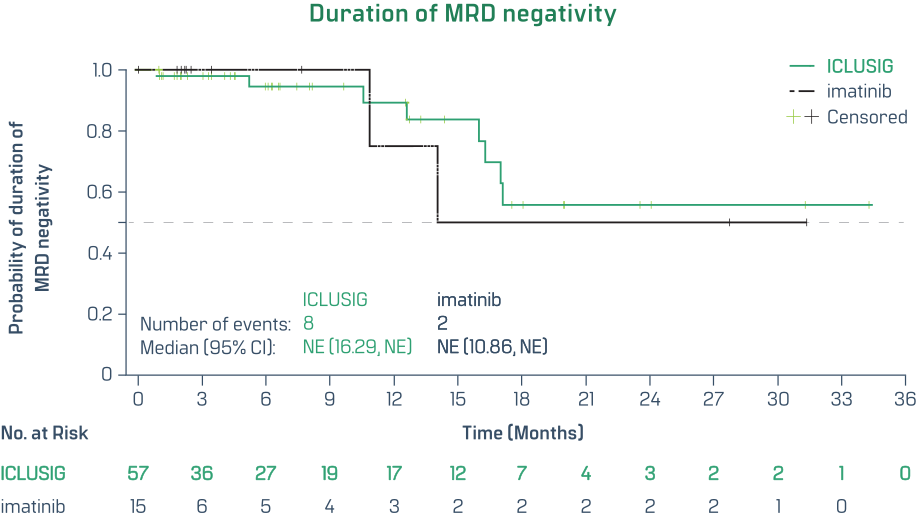
Durable MRD negativity with ICLUSIG (additional endpoint)2-4
- Study features3,4
- Relapse from MRD negativity: 14% (n=8) of ICLUSIG patients vs 13.3% (n=2) of imatinib patients at the time of data cutoff (August 12, 2022)
- Limitations: PhALLCON was designed to show a statistically significant difference between arms for MRD-negative CR;‡ the trial was not designed to show a statistically significant difference between arms for duration of MRD negativity
‡MRD negativity was defined as ≤0.01% BCR:ABL1/ABL1 or undetectable BCR::ABL1 transcripts in cDNA with ≥10,000 ABL1 transcripts. BCR::ABL1/ABL1 levels were reported as an absolute (raw) ratio for the p190 variant test and on the International Scale (BCR::ABL1IS) for the p210 variant test.3
cDNA=complementary DNA; CI=confidence interval; CR=complete remission/response; MRD=minimal residual disease; NE=not evaluable


